Eastern Europe has been part of international clinical development for years. Research centers there take part in multinational studies across a wide range of therapeutic areas. But treating the region as one clinical research market invites unrealistic assumptions. Healthcare structures differ between countries. So do regulatory environments, investigator networks, patient referral pathways, and site capabilities.
Executing Eastern European clinical trials requires matching protocol requirements to country-specific clinical practice, mapping patient referral pathways into centralized specialist centers, verifying site diagnostic and staffing capacity against competing studies, sequencing regulatory and laboratory start-up dependencies before activation, and applying consistent risk-based quality monitoring across all participating markets.
A CRO in Eastern Europe therefore has to pair regional coordination with country-specific operational knowledge. Sound study planning rests on knowing where appropriate patients are treated, which institutions hold the required capabilities, and how local research processes fit the wider international development strategy.
Country Selection Requires Study-Specific Analysis
Whether a given country suits a study depends heavily on the protocol. Disease prevalence matters, but it is only one component of feasibility. Eligibility criteria, standard treatment pathways, diagnostic practices, competing studies, and access to specialized procedures can all shrink the population realistically available for recruitment.
Country assessment should therefore test how the protocol fits local clinical practice. Take a study requiring advanced molecular diagnostics. It may need to focus on specialized institutions over a large network of general treatment centers.

Done properly, this approach establishes realistic recruitment assumptions before resources go toward regulatory preparation and site activation.
Understanding Patient Access
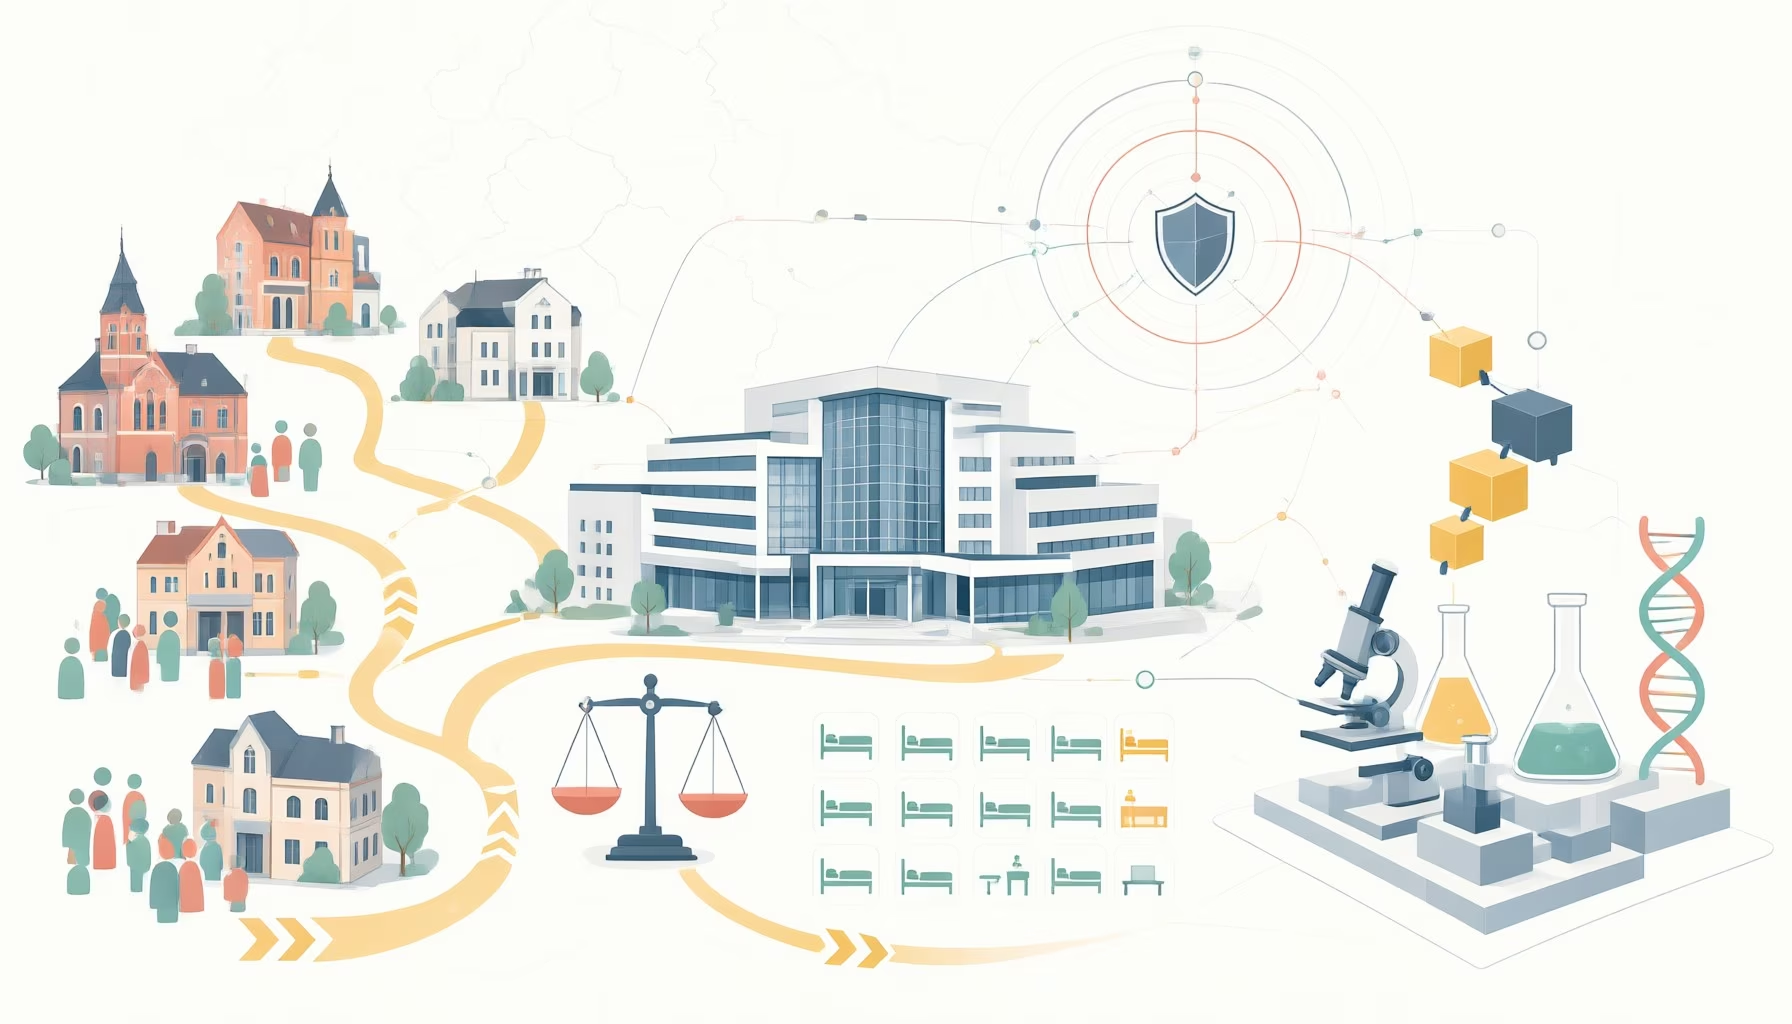
One potential strength of some Eastern European research markets is the presence of centralized specialist institutions treating substantial numbers of patients. Patient volume alone, though, does not predict enrollment.
Referral pathways determine where individuals receive diagnosis, specialist consultations, and treatment. Potential participants may first present at regional hospitals before being referred to larger academic or specialist centers. In other therapeutic areas, care may stay decentralized.
A CRO in Eastern Europe can build knowledge of these pathways into feasibility assessments. Understanding how patients move through the healthcare system helps identify sites with genuine access to the protocol-defined population, moving beyond exclusive reliance on investigator estimates.
Empirical industry benchmarks reinforce why sponsors invest in mapping these local structures. According to Applied Clinical Trials Online research on Eastern European site management, over 43% of survey respondents confirmed they would definitely include Eastern European clinical sites in their trials because centers deliver fast enrollment, high patient retention, and strong data quality despite complex local legal agreements and administrative workloads. Similarly, Clinical Trials Arena reporting with Novotech regional director Nick Rich notes that trial volume in Central and Eastern Europe nearly doubled between 2021 and 2023 as sponsors sought reliable recruitment capacity within a broader European market that Market Research Future projects to grow from USD 16.05 billion in 2025 to USD 18.4 billion by 2035. The table below outlines how different patient referral models shape site feasibility and recruitment planning.
| Referral Pathway Model | Clinical Care Structure | Operational Implication for Enrollment | Key Feasibility Verification Check |
|---|---|---|---|
| Centralized Specialist Model | Patients with complex or specialized conditions are routed to national or regional academic reference centers. | Concentrates eligible participants at fewer high-volume investigative sites, supporting rapid screening when diagnostic criteria match local standards. | Confirm whether patients arrive pre-diagnosed or require protocol-specific molecular or imaging workups on site. |
| Regional-to-Academic Referral Model | Patients present initially at community or district hospitals before referral to tertiary specialist clinics for advanced therapy. | Enrollment depends on active communication between referring physicians and the investigative site team. | Verify existing referral links between surrounding regional hospitals and the principal investigator’s department. |
| Decentralized Outpatient Model | Ongoing disease management stays distributed across local outpatient clinics and primary or secondary care practices. | Single academic centers capture a smaller share of the total patient pool, requiring broader site networks. | Assess whether outpatient centers have the staffing, pharmacy storage, and administrative support required by the protocol. |
Evaluating Investigative Sites
Site selection should weigh recruitment potential alongside operational capability. Research centers need sufficient staff, appropriate facilities, and experience with the procedures the study requires.
Depending on the protocol, qualification may include reviewing pharmacy arrangements, laboratory capabilities, imaging equipment, sample storage, emergency facilities, technology access, and previous clinical research experience.
Competing trials deserve scrutiny too. An experienced investigator may look attractive during feasibility yet have limited capacity if several studies are recruiting from the same patient population.
Sometimes fewer well-qualified centers deliver greater operational value than a large number of sites with uncertain recruitment potential.
Coordinating Regional and Central Teams
Multinational studies require local activities to stay aligned with global project objectives. Country teams communicate with investigators and institutions. Central teams oversee overall timelines, quality indicators, safety processes, and cross-country performance.
Clear allocation of responsibilities matters most when a study spans several markets. Regulatory specialists, clinical research associates, project managers, data teams, and safety professionals all need established communication and escalation pathways.
Regional coordination can surface issues that extend beyond an individual site. Similar recruitment difficulties or protocol deviations across several countries, for example, may point to a broader study-level problem beyond isolated site performance.
Managing Start-Up Dependencies
Study activation depends on multiple activities progressing in the correct sequence. Regulatory and ethics requirements, institutional documentation, contracts, budgets, translations, investigational product logistics, laboratory setup, and system access can all influence the date a center begins screening participants.
Map these dependencies during project planning. A site that has completed training cannot enroll if laboratory materials are unavailable. Completed contracts provide limited value if essential regulatory requirements remain unresolved.
A realistic start-up strategy therefore considers the complete activation pathway without measuring individual milestones in isolation.
Monitoring Actual Performance

Once enrollment begins, actual study data should replace assumptions made during feasibility. Screening activity, enrollment rates, screen failures, protocol deviations, safety reporting, data queries, and participant retention all provide information about site performance.
Risk-based oversight lets teams concentrate resources where emerging signals indicate potential concerns. Centralized review can identify patterns across countries. Targeted monitoring can investigate issues at specific centers. As documented in Applied Clinical Trials Online, shifting to risk-based monitoring models with fewer on-site visits can strain Eastern European centers that have limited internal administrative staff, making proactive support from local clinical monitors essential.
An experienced CRO in Eastern Europe can also provide context for these indicators. A change in performance may reflect site-level difficulties, shifts in local treatment practice, competing research, or broader protocol-related challenges.
Maintaining Quality Across Different Markets
Regional diversity should not produce different standards for participant protection or data integrity. Common study procedures, monitoring expectations, documentation standards, and quality controls need to apply across all participating countries.
At the same time, operational implementation may require adaptation to local institutional processes. The objective is to preserve the requirements of the protocol and quality system while allowing practical workflows to reflect each country’s research environment.
Continuous Trial Master File maintenance, documented decision-making, and timely issue escalation support traceability throughout the study lifecycle.
FAQ
How do you select countries for a clinical trial in Eastern Europe?
Feasibility assessments must verify disease prevalence, eligibility criteria, standard treatment pathways, local availability of molecular or imaging diagnostics, competing trials recruiting from the same population, and the operational staffing of investigative sites before regulatory submissions begin.
What should sponsors know about patient access in Eastern Europe?
Many Eastern European countries treat complex conditions within centralized specialist institutions, which concentrates patient volume at major academic centers. However, actual trial enrollment depends on local referral pathways from regional hospitals and whether decentralized outpatient clinics retain care for the target indication.
Eastern Europe should be approached as a collection of distinct clinical research environments, never as a uniform operational market. A CRO in Eastern Europe can connect regional project governance with knowledge of local healthcare systems, investigator networks, patient pathways, and site capabilities. Protocol-driven country selection, evidence-based feasibility, coordinated start-up, and continuous performance assessment provide a practical foundation for integrating Eastern European research centers into multinational clinical development while maintaining consistent standards for quality and participant protection.